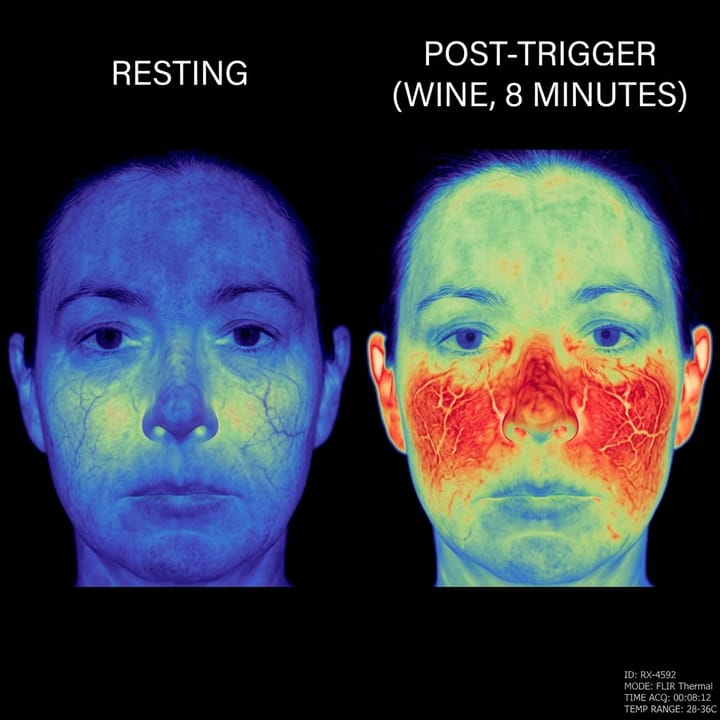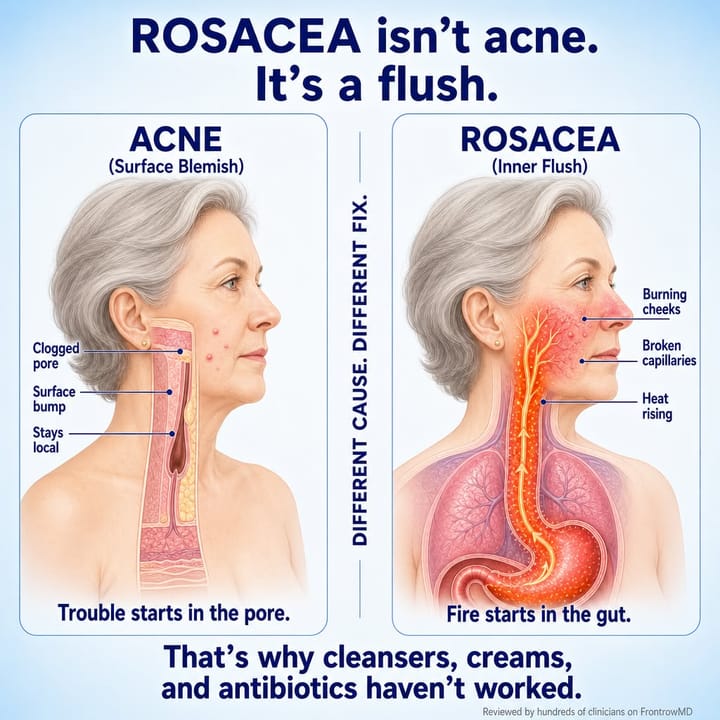
I've treated rosacea in Germany for 18 years without long-term metronidazole. When I moved to America, I couldn't believe what dermatologists here were telling their patients. I've been a dermatologist for 20 years. The first 18, I practiced in Munich. I moved to the United States two years ago when my husband's company transferred him to Boston. I joined a dermatology practice here. Good practice. Good doctors. And in my first three months, I saw something that kept me up at night. Women in their 50s and 60s coming in with red, burning, bumpy faces they'd been fighting for a decade. Cheeks on fire. Broken capillaries. Pustules they couldn't cover. Every one of them said the same thing. "My dermatologist has been managing it for years." Managing it. In Germany, we don't manage rosacea progression while prescribing creams that can't reach the cause. We address the inflammatory loop driving it from inside the body. Because by the time the redness has spread across the cheeks, nose, chin, and forehead, something has already failed — structurally, systemically — and painting another cream on the surface won't fix that. It only suppresses what's already burning underneath. Here's what your dermatologist probably hasn't told you about what chronic rosacea actually is. Your face is not where the fire starts. It's where the fire shows up. Rosacea is a self-sustaining inflammatory feedback loop, and the visible redness is the smoke at the end of a three-layer process happening inside your body. When you apply a cream on top, it works on the smoke. The cytokines being manufactured deep in the skin — driven by an enzyme called KLK5 — keep firing. The bacterial fragments leaking from your gut into your bloodstream keep activating the same inflammatory alarm. The hormonal anti-inflammatory brake your body lost at perimenopause keeps staying gone. But that's only the first layer. The inflammation itself has built a self-reinforcing cycle — the byproducts of each flare become the inputs for the next one — that makes the loop up to 100 times more resistant to whatever surface treatment gets through. Three layers. Gut bacteria pumping fuel into the bloodstream. Inflammatory cytokines firing inside the skin. Estrogen collapse removing the natural brake. No amount of cream cuts the fuel line. Topical antimicrobials kill surface-level bacteria and mites on exposed skin — they were never designed to reach a gut bacterial overgrowth, suppress systemic cytokines, or replace a hormonal brake. So the loop keeps spinning. The cytokines recruit more inflammatory cells. Adjacent vessels dilate. New broken capillaries form. And your dermatologist keeps prescribing creams and telling you to be patient. Peer-reviewed dermatology research has documented for years that systemic inflammatory drivers — not topical treatment strength — are what drive chronic rosacea persistence in patients with otherwise consistent compliance. Not poor skincare. Not wrong cleanser. Systemic inflammatory drivers. Your compliance isn't the problem. The protocol treating compliance as the solution is. I want to be honest about long-term oral antibiotics. Because most of my Boston patients had been told doxycycline or oral metronidazole was their next step. Some had already done it. Some had done it twice. Doxycycline enters the bloodstream — which is the correct delivery route. It bypasses the limitations of topical creams. It reaches the inflammatory cascade from inside. What it can't do is fully break the loop before the recurrence window opens. Doxycycline partially suppresses inflammatory signaling. When the three-month course ends — because long-term oral antibiotic use carries microbiome disruption, photosensitivity, and antibiotic resistance risks — the loop rebuilds. The cytokines re-fire. 60-70% recurrence within twelve months. Doxycycline is like draining a flooded basement while the pipe is still leaking. The water goes down. For a while. I've seen it in patients who came to me after doxycycline. Good initial response. Maybe a few months of clearer skin. And 8 months later, the redness creeping back across the cheeks. Because nothing had permanently cut the fuel line. This is what nobody tells you about where untreated systemic inflammation leads. It doesn't stay behind a few flushes a week. The inflammatory loop doesn't just stay constant — it amplifies. Each flare damages the skin barrier. Each barrier breach lets more triggers in. Each new trigger fires the cascade again. Each new cascade builds new fragile capillaries. Two flares a week at age 45 can become daily flushing by age 48. Persistent redness by 50. Fixed broken capillaries and visible vessels by 55. I've had the conversation that follows more times than I should have. With women who did everything their dermatologist told them. Who applied ivermectin every night for years. Who never missed a single application. Who still, over time, watched the redness spread from cheeks to nose to chin to forehead. The cream addressed the surface. The loop underneath kept advancing. Silently, systematically — until the damage wasn't patchable with topicals anymore and the only options left were repeated rounds of oral antibiotics or expensive laser sessions every six months for life. When I arrived in the US, I assumed the research on systemic loop interruption simply hadn't made it here yet. In Germany, we'd been working with lipid-soluble botanical protocols for over a decade. It emerged from European dermatology and gastroenterology research in the early 2010s — clinicians studying why some patients responded to standard treatment and others didn't, despite identical protocols. What they found was that non-responders had significantly higher rates of underlying SIBO, H. pylori, and inflammatory cytokine load. The doxycycline couldn't fully break the loop before the treatment window closed. It wasn't drug failure. It was loop failure. That research led to trials on whether interrupting the loop with lipid-soluble botanical compounds — specifically carvacrol from oregano oil — could clear chronic rosacea without long-term oral antibiotics. In cases where the inflammatory loop was the primary barrier, not drug resistance. Published research documented direct cytokine suppression and SIBO clearance with carvacrol at 70%+ concentration. The fuel line is cut at the source. Through the bloodstream. Past the limits of any topical. To the inflammatory cascade from the only direction the loop can't keep firing through. Combined with thymoquinone from black seed oil — which directly suppresses IL-6, IL-12, and TNF-α and provides a portion of the anti-inflammatory tone estrogen used to deliver — the protocol cuts the fuel line AND restores the hormonal brake the body lost at 45. No liver toxicity. No three-month forced stopping point. Continuous delivery until the loop has fully unwound. I want to tell you about one patient. Because her results are what I see when people finally address the right barrier. She was 56. Had been on topical protocols since 49. Cheeks, nose, and chin all involved. Persistent flushing. Pustules. Her previous dermatologist had recommended a long-term doxycycline maintenance protocol. She came to me for a second opinion. Her compliance was perfect. The rosacea was real. The inflammatory loop was the barrier. In Germany, before we ever reach for long-term oral antibiotics, we ask one question: have we addressed the loop? Doxycycline partially suppresses the cascade. It doesn't break it. I recommended 90 days of systemic loop interruption before making any antibiotic decisions. She was skeptical. Seven years of perfect compliance hadn't produced one stretch of stable, calm skin. She didn't believe capsules could change what seven years of creams hadn't. I explained it simply. Cream sits on the surface of the smoke. That's what it does. It does not reach the gut, the bloodstream, or the hormonal layer. Your face isn't getting worse because the cream is weak. It's getting worse because the loop is intact and the treatment can't reach the cause behind it. You can paint a wall perfectly. If the pipe behind it is still leaking, the damage keeps coming back. She agreed to try. Orgatics Oregano & Black Seed Oil. Pharmaceutical-grade. 70%+ standardized carvacrol. Cold-pressed thymoquinone. Two capsules with breakfast. Week 1: Burning sensation calmer across all affected areas. The constant heat she'd carried for years — visibly reduced. Week 2: First mornings without an automatic flush. The bloating she'd had for years — gone. The first time she'd seen her actual skin tone underneath in seven years. Week 4: Pustules flattening on five different zones. The crumbling, dry, reactive texture had stopped. Skin holding moisture again. Week 8: Over 50% reduction in baseline erythema. The flushing episodes had stopped. No new pustules. Week 12: Her dermatologist — her previous one, the one who recommended the doxycycline maintenance — measured the erythema score. Then measured again. "The inflammation is completely resolved. Healthy barrier function. No active rosacea involvement." She didn't need long-term doxycycline. She didn't need laser maintenance. In Germany, this is where we start. Not with antibiotics for life. With the loop. I share this because I spent two years quietly frustrated by what I see here. Women who came to me after years of being told to keep applying — while their loop silently spread from cheeks to nose to chin. Women who felt like they were failing. Like their bodies were betraying them despite perfect compliance. They weren't failing. The protocol was failing them. American dermatology training focuses on topical protocols and oral antibiotic escalation. Systemic loop interruption — addressing the actual fuel line — isn't part of standard training. Most American dermatologists graduated before this research was emphasized. They practice what they were taught. That's not a criticism. It's just where the knowledge gap sits. But the research exists. And you don't have to wait for your dermatologist to find it. If you've been applying creams for months or years with no lasting clearing — if you've done oral antibiotics and watched the redness come back — if you've been told your rosacea is "just chronic" but your compliance has been perfect — The answer isn't to apply more consistently. It's to cut the fuel line your treatment was never designed to reach. I'll leave a link below to the product I recommend to my own patients. I have no financial relationship with this company. I recommend it because the mechanism is sound, the research supports it, and I've seen it work. You've spent years doing what you were told. It's time to address what you were never told. 90-day money-back guarantee. Two capsules with breakfast. No complicated routine. Your face isn't failing you. The protocol treating your compliance as the problem is what's failing you. The loop is the barrier. Cut the fuel line.
Read more